
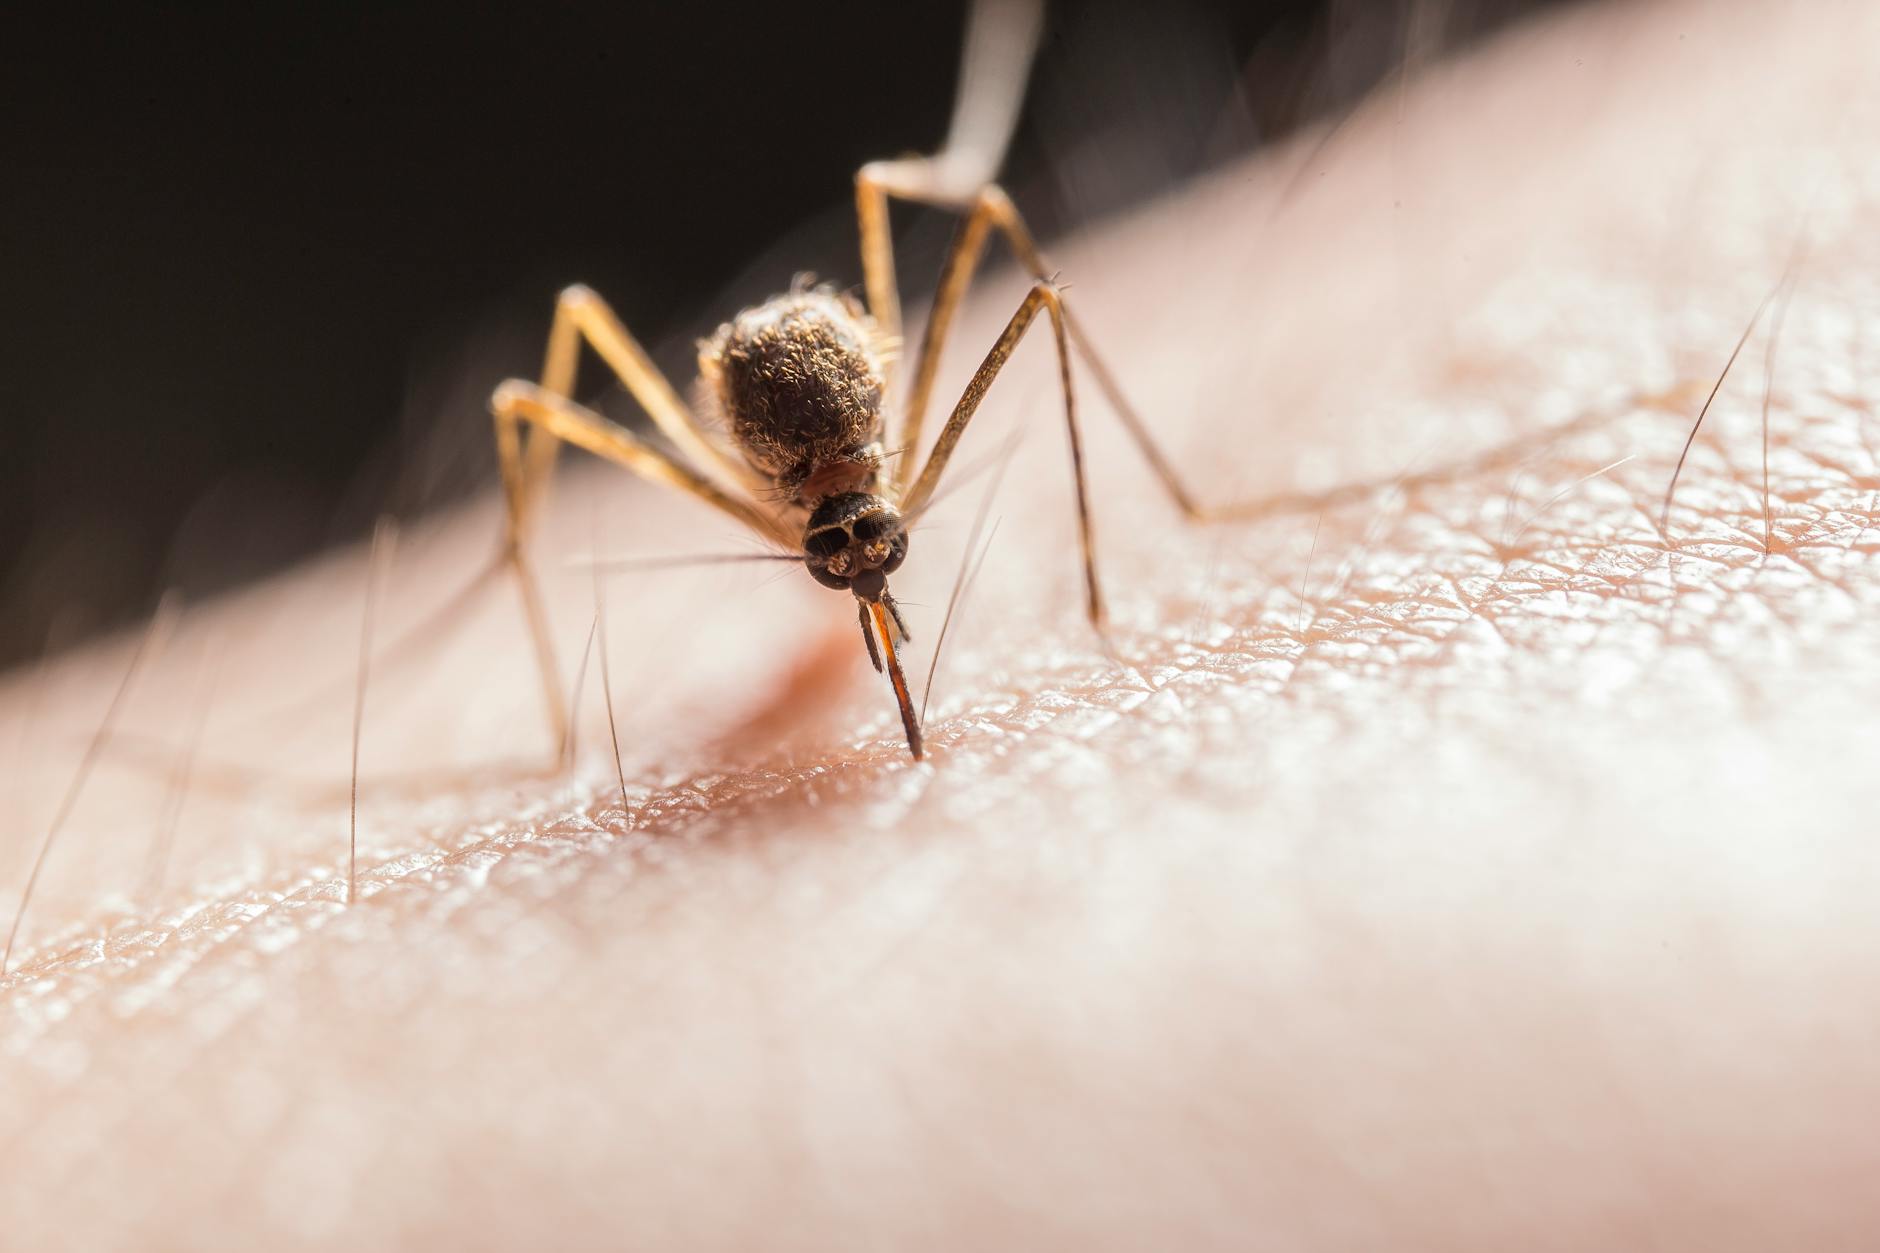
Understand mosquito-borne disease pathways, warning signs and practical prevention while checking current Florida health advisories.
Local mosquito abundance and infection risk are different
Florida’s warm conditions, rain and water-holding sites support mosquito activity, but many mosquitoes are nuisance species. A mosquito population increase does not by itself establish a disease outbreak. Infection risk also depends on the mosquito species, whether the pathogen is present and the local transmission cycle.
Check the Florida Department of Health’s current arbovirus surveillance and county health information for local activity. Its reports distinguish surveillance findings and different diseases over time. A past outbreak, an imported case and current local transmission should not be treated as the same event.
Use current local advisories to assess exposure. A national severity statistic or a dated outbreak headline cannot predict the risk on a particular property.
Which mosquito groups matter?
Florida’s container-breeding Aedes include the yellow fever mosquito, Aedes aegypti, and the Asian tiger mosquito, Aedes albopictus. Both are important vector species, but their presence alone cannot establish dengue or Zika transmission. Their immature stages develop in water-holding containers; removing these sites addresses development rather than just the adults that happen to be flying. Culex mosquitoes, including the southern house mosquito Culex quinquefasciatus, can be West Nile vectors. Anopheles mosquitoes transmit malaria when the relevant parasite is present. The presence of a species does not establish that its individual members are infected.
Eastern equine encephalitis has a more complex cycle. Culiseta melanura primarily participates in transmission among birds in swamp habitats and is not considered the main human-biting vector. Other mosquito species can act as bridge vectors between infected birds and mammals. Listing only Culiseta melanura in a human-disease table would hide that distinction.
Protect yourself throughout the day and evening. Different species have different biting patterns, and advice restricted to dusk and dawn misses some exposures. A homeowner cannot determine infection status from the mosquito’s stripes, size or the look of a bite.
Mosquitoes develop through egg, larva, pupa and adult stages. Larvae and pupae occupy water, while flying adults use resting sites in the surrounding landscape. Species use different container, floodwater or permanent-water habitats. Removing a refillable container and maintaining a screen therefore address different stages; neither requires altering a natural wetland.
Culex nigripalpus also warrants species-specific identification and habitat assessment. UF/IFAS lists it among mosquitoes that can occasionally occupy containers or treeholes, while being more abundant in their preferred habitats, and among species that can transmit multiple arboviruses causing human disease. This is species biology, not evidence of infection or an outbreak on your property. Ask the local mosquito program or provider to identify the observed mosquito and relevant habitat rather than assigning every container mosquito the same disease role.
West Nile virus and eastern equine encephalitis
Most people infected with West Nile have no symptoms. Some develop fever, headache, body aches, gastrointestinal symptoms or rash. Severe illness can involve the nervous system, with neck stiffness, confusion or weakness. Risk of severe illness increases with factors such as age, some chronic conditions and weakened immunity, but anyone can be affected.
Eastern equine encephalitis is rare but can be serious. Symptoms can include fever, headache, vomiting, seizures, behavior changes and drowsiness. People who develop severe EEE can die or have lasting neurologic effects. Severe disease is different from receiving a mosquito bite or having an asymptomatic infection, so individual risk cannot be inferred from one insect encounter.
Serious neurologic symptoms require urgent medical attention. These viral illnesses do not have a universal household cure, and antibiotics do not treat the viruses. Healthcare professionals determine testing and supportive treatment; a pest-control visit cannot diagnose or eliminate an existing infection.
Dengue: watch for deterioration after fever improves
Dengue can cause fever with headache, pain behind the eyes, muscle or joint pain, nausea and rash. Symptoms overlap with other illnesses, so a bite mark or symptom chart cannot establish the diagnosis. Tell a clinician about recent travel, local exposure and when the illness began.
Warning signs of severe dengue include significant belly pain, repeated vomiting, bleeding from the nose or gums, blood in vomit or stool, and marked tiredness or restlessness. Seek immediate medical care for warning signs. They can appear after fever goes away, so an improving temperature alone is not proof of recovery.
“Dengue hemorrhagic fever” should not be used as a catch-all description of every complication. Severe dengue can involve shock or bleeding. Evaluation and treatment decisions belong with healthcare professionals rather than a pest-management checklist.
Zika and malaria: distinguish current exposure from history
Zika can be asymptomatic or cause relatively mild fever, rash, aches and red eyes, yet infection during pregnancy can cause serious birth defects. It can also spread through sex and to a fetus during pregnancy. Pregnant people or those planning pregnancy should review possible exposure and current guidance with their clinician.
An Aedes mosquito sighting is not evidence of active Zika transmission. Historical local transmission does not establish a current outbreak, and yard treatment cannot address every route of Zika exposure.
Malaria is caused by parasites and is not endemic in the United States. Most U.S. cases involve travel, although rare local transmission can occur. Florida’s historical local-malaria reports should be read as dated events, with current surveillance checked separately.
Fever after travel to a malaria area warrants prompt medical evaluation, including travel within the previous year. Do not wait for a perfectly cyclical fever pattern. Untreated malaria can become severe, and diagnosis and prescription treatment depend on the actual infection.
The malaria comparison also needs recognizable illness clues. CDC lists fever and flu-like illness, chills, headache, muscle aches and tiredness as early symptoms; nausea, vomiting or diarrhea can occur. Untreated infection can progress to severe illness such as kidney failure, seizures, confusion or coma. These symptoms overlap other diseases and do not diagnose malaria at home. Seek medical assessment for illness after a relevant exposure or travel history rather than waiting for a cyclical fever pattern; Florida’s historical local cases are not proof of a current outbreak.
Compare symptoms without turning the chart into a test
West Nile and EEE can involve neurologic illness; dengue can deteriorate with warning signs after fever falls; Zika has particular pregnancy and sexual-transmission concerns; malaria requires prompt recognition of relevant travel or exposure. Fever and aches overlap across these diseases and many unrelated illnesses.
Seek medical advice for illness after possible exposure. Severe dengue is a medical emergency. Seek immediate care for dengue warning signs, including severe abdominal pain or tenderness, repeated vomiting, bleeding, or marked tiredness or restlessness; warning signs can develop as fever goes away. Share the timeline and geographic history rather than asking a pest provider to identify the disease from the insect.
No disease should be labeled universally “most dangerous” without defining severity, frequency and the person at risk. Rarity and severity are different measures, and neither supplies a neighborhood ranking.
Prevent bites and maintain the home
Use an EPA-registered repellent labeled for the user and intended protection, and follow application and reapplication directions. CDC lists DEET, picaridin, IR3535, OLE, PMD and 2-undecanone as options. OLE and PMD should not be used on children under three. Homemade essential oils do not have equivalent evidence for disease prevention.
Wear loose-fitting long sleeves and pants. Clothing or gear can be treated with permethrin as directed, but permethrin should not be applied directly to skin. Use intact window and door screens, close unnecessary openings and use air conditioning when available.
At least weekly, empty and scrub, turn over or cover water-holding items such as buckets, toys, flowerpot saucers and birdbaths. Inspect items that refill after rain or irrigation. Water that cannot be removed may need site-appropriate labeled larval control; drinking water, shared drainage and natural habitat require different decisions.
Include roof drainage in the water inspection. UF/IFAS recommends cleaning eaves and gutters; check accessible downspout outlets and drainage paths for debris that prevents water moving away. Arrange safe maintenance for elevated gutters or places you cannot reach, and limit work to your own property or obtain the responsible party’s help. A container checklist alone can miss these drainage sites, while cleaning them does not stop every mosquito arriving from elsewhere.
Sleeping-area protection is a separate barrier task. UF/IFAS recommends mosquito netting around the bed when windows lack screens, so an unscreened sleeping space needs more than an assumed air-conditioning benefit. Use appropriate intact netting with the sleeping setup’s instructions, alongside screens, clothing and registered repellents where applicable. Netting reduces access at that sleeping site; it does not eliminate outdoor breeding or certify disease prevention.
Include natural water holders in the inspection conversation: tree holes and the tanks or leaf axils of bromeliads can support immature mosquitoes, alongside artificial pots, tires and other containers. UF/IFAS treats these plant-held waters as distinct habitats. Check accessible plant water and discuss suitable maintenance with Extension or the mosquito program; do not damage a tree, remove a valued plant or apply a pesticide to a natural water site by assumption. Finding larvae alone does not identify the species or establish a disease risk.
Know what professional mosquito control can add
A qualified provider or local mosquito-control district can assess sources and suitable management. Adult treatments and larval-source measures address different stages. A trap system also has placement and servicing requirements; no one method establishes complete removal of infected mosquitoes or guaranteed disease prevention.
Report persistent activity or inaccessible public sources to the appropriate local authority. Do not alter wetlands, shared drainage or neighboring property yourself. Ask what the proposed plan reaches and what household maintenance remains necessary.
Keep personal protection and screens in place after service. Mosquitoes can arrive from beyond a property, and disease risk changes with public-health findings. A written site-specific plan and current advisories are more useful than a fixed monthly protective-barrier promise.
A documented station mechanism is more specific than a generic trap promise. The EPA-accepted July 2024 In2Mix-R label describes females contacting treated powder after egg laying and transferring an insect growth regulator to additional water sites where it affects larvae before they become adults. This transfer role differs from an adult-contact spray or an ordinary insect monitor. It is a bounded product-label example, not proof that every trap uses the same mechanism, that current permissions are unchanged, that ODPC offers it or that a station prevents disease. Confirm the actual product, permitted use, placement and maintenance before comparing it with other tools.
Sources
- CDC: mosquitoes in the United States
- Florida DOH: arbovirus surveillance
- CDC: EEE transmission cycle
- UF/IFAS: Florida container mosquitoes
- UF/IFAS: Florida mosquitoes and IPM
- CDC: malaria
- CDC: West Nile virus
- CDC: eastern equine encephalitis
- CDC: dengue symptoms and warning signs
- CDC: Zika
- CDC: preventing mosquito bites
- CDC: Mosquito Control at Home
- EPA: integrated pest management
Frequently asked questions
-
What is the most dangerous mosquito-borne disease in Florida?
There is no universal ranking without defining severity, frequency and individual vulnerability. EEE can be severe but is rare; other infections have different patterns. Check current local advisories and seek care for concerning symptoms after exposure.
-
Can you get malaria from mosquitoes in Florida?
Rare local transmission is possible, but malaria is not endemic in the United States and most U.S. cases relate to travel. Historical Florida cases do not establish current local transmission. Review current health information and seek prompt care for fever with relevant exposure.
-
When is mosquito-borne disease risk highest in Florida?
Activity and disease risk depend on species, conditions and current local transmission. Warm and rainy periods can increase encounters, but a fixed June-through-October window cannot define all Florida risk. Use precautions when exposed and check current advisories.
-
How can I tell if a mosquito bite has given me a disease?
A bite mark cannot diagnose infection. Seek medical advice for fever or illness after exposure and share travel and timing. Neurologic symptoms or dengue warning signs require urgent care, including when fever has improved.
-
Do all mosquitoes in Florida carry diseases?
No. Only some species can transmit particular pathogens, and an individual must be infected for the relevant transmission pathway. Infection status cannot be read from appearance. Prevention remains useful because you cannot assess it at a bite.
-
Is professional mosquito control effective against disease-carrying mosquitoes?
Appropriate source management and labeled treatment can reduce mosquitoes in targeted sites, but no property service guarantees disease prevention. Adults may arrive from elsewhere. Continue repellent, screens and maintenance and follow public-health guidance.
Get help with your pest concern.
Tell us what you are seeing. Our team can discuss the concern and the next step.
- Share your concern and contact details.
- Our team contacts you to discuss available service.
- Ask for a written scope and quote before work.
Where can we reach you?
Our team will call to confirm the next step.
By submitting, you’re asking On Demand Pest Control to contact you about this request.
↗ Prefer to call? (954) 947-0805